
PACS System in Radiology: How It Works and What Hospitals Should Consider
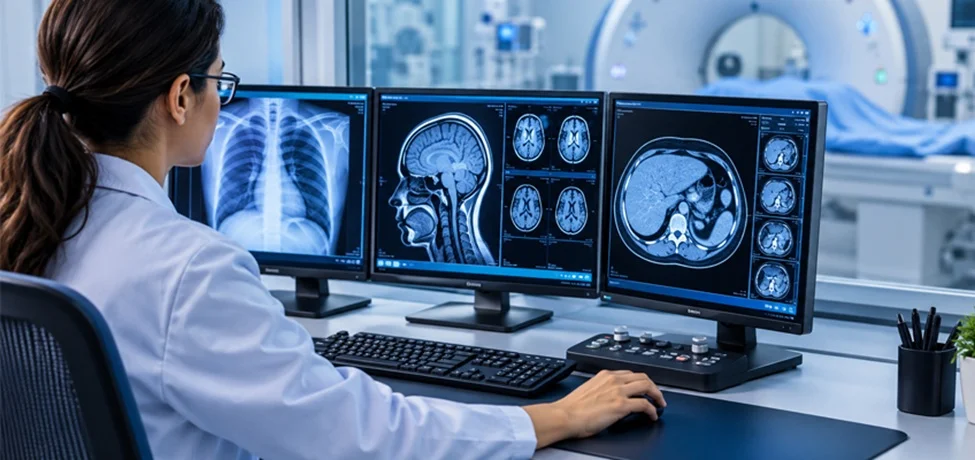
A PACS system (picture archiving and communication system) is the technology hospitals and imaging centers use to store, retrieve, share and view medical images such as X-rays, CT scans, MRIs and ultrasounds. It replaced physical film with secure digital access, so radiologists and referring doctors can view the same study in seconds from any authorized workstation. This guide explains how a PACS system works in radiology, its main components, where cloud PACS fits, and what hospitals should consider when choosing one.
For a hospital or imaging center, choosing a PACS is not a small decision. It touches every radiologist, technologist and referring physician you have.
What Is a PACS System?
PACS stands for picture archiving and communication system. In plain terms, it is the technology that stores, retrieves, distributes and displays medical images. Instead of printing an X-ray on film and walking it down the hall, the image goes from the scanner to a secure server, and any authorized clinician can open it in seconds.
PACS in radiology became standard because it solved real daily problems: lost films, slow reporting, duplicate scans and expensive storage rooms. Today, PACS medical imaging covers far more than radiology, including cardiology, orthopedics, oncology and more, though radiology remains its home.
How PACS in Radiology Actually Works
The workflow is simpler than the jargon suggests:
1. Acquisition. A patient is scanned on a CT, MRI, X-ray or ultrasound machine, called a modality.
2. Transfer. The modality sends the images to the PACS using DICOM, the universal imaging standard.
3. Storage. The PACS archives the study and links it to the patient's record.
4. Viewing. A radiologist opens the study on a diagnostic workstation, scrolls through slices, measures, compares with prior exams and writes a report.
5. Sharing. The report and images reach the referring doctor, often through the hospital information system or an electronic health record.
Most of the value is in steps four and five. Radiologists read faster when priors load automatically, and referring physicians stop calling the department asking, "Is the report ready?"
Are DICOM and PACS the Same?
No. DICOM (Digital Imaging and Communications in Medicine) is the language; PACS is the system that uses it. DICOM defines how images and their patient details are formatted and exchanged between devices. A PACS is the platform that receives, stores and displays those DICOM files. You can think of DICOM as the file standard and PACS as the library that holds the books.
What Are the Four Main Components of a PACS System?
Most descriptions break it down into four parts:
- Imaging modalities: the scanners that create the images (X-ray, CT, MRI, ultrasound, mammography).
- Network: the secure connections that move studies between devices, servers and workstations.
- Archive and storage: the servers, local or cloud, where studies are kept and backed up.
- Workstations and viewers: the diagnostic monitors and software radiologists use to read, plus lighter viewers for clinicians.
Some lists add RIS integration or a reporting layer as a fifth piece, but these four are the foundation.
Is PACS Hardware or Software?
Both, historically. Older systems needed on-site servers, storage arrays and dedicated workstations, so people thought of PACS as equipment. Now the intelligence sits in the PACS software, and the hardware can be your own data center, a managed host or the cloud. When vendors say "PACS," they usually mean the software platform, with hardware as a deployment choice.
X-Ray PACS and Ultrasound PACS: Different Needs, Same Backbone
Not every modality behaves the same way, and that matters when you evaluate a vendor.
An x-ray PACS system handles high volumes of relatively small studies. Speed and workflow matter most: hundreds of chest and bone images a day need to hit the worklist fast, with simple tools for windowing, annotation and comparison. Digital radiography has made this the entry point for many smaller hospitals.
Ultrasound PACS is trickier. Ultrasound produces cine loops, measurements and structured reports, and sonographers often scan at the bedside or in clinics. Your system should handle multi-frame clips, store measurements correctly and fit the way your sonographers actually work. If a vendor demonstrates only CT and X-ray, ask to see ultrasound too.
Cloud-Based PACS: What Changed
For years, a PACS meant servers in your basement and an IT team to babysit them. Cloud based PACS moves the archive, and often the application itself, to a secure hosted environment. Studies are accessed through a browser or thin client.
Why hospitals are choosing it:
- Lower upfront cost, since you aren't buying servers.
- Easier disaster recovery and automatic backups.
- Remote reading for teleradiology and after-hours coverage.
- Simpler scaling when study volumes grow.
- Fewer upgrade headaches, because the vendor handles them.
What to watch:
- Internet reliability. Large studies need decent bandwidth, so plan for it.
- Data residency and privacy rules in your country or state.
- Ongoing subscription costs that add up over a decade.
- Exit terms. Know how you'll get your data back if you leave.
Is PACS SaaS?
It can be. Many modern vendors offer PACS as a subscription service, which is software as a service. Others still sell traditional licenses for on-premise installs, and some offer hybrid setups where recent studies stay local and older ones sit in the cloud. SaaS is an option, not a rule.
What Is the Difference Between PACS and VNA?
This one confuses a lot of buyers. A PACS is built mainly for radiology workflow: reading, reporting and short-term access. A vendor neutral archive (VNA) is a long-term, standards-based storage layer that can hold images from many departments and many PACS products at once.
The key word is neutral. If your archive is locked inside one PACS vendor's proprietary format, switching vendors can mean painful, expensive migrations. A VNA keeps your data in open formats, so the viewer can change while the archive stays put. It also helps health systems with multiple hospitals that run different PACS platforms.
Not every facility needs one. A single small imaging center may be fine with a well-chosen PACS. A multi-site hospital group, or one planning to change vendors, will find a VNA valuable.
What Is PACS Now Called?
The term PACS is still widely used, but you'll hear newer labels too: enterprise imaging platform, cloud imaging, or medical image management. These describe a bigger scope. Modern platforms handle not just radiology but also photos, videos, scanned documents and other "-ologies" in one place, often with AI tools built in. The old PACS name remains common because buyers still search for it, and vendors still use it.
Choosing PACS Software and PACS Vendors
There is no single best PACS system for a hospital, because the best choice depends on your size, specialties, budget and IT capacity. A 40-bed community hospital and a multi-site academic center need very different things. Still, a few questions help every buyer.
Look at the radiologists' experience first. If your readers hate the viewer, nothing else will matter. Let them test it with real studies, not a polished demo.
Check integration. Can it connect smoothly with your RIS, EHR, HIS and reporting tools? Does it support standards like DICOM, HL7 and FHIR? Poor integration creates daily friction.
Ask about performance at your scale. How does it perform with your study volume, your largest datasets and your remote readers?
Review security and compliance. Look for encryption, audit trails, role-based access and compliance with the rules that apply to you, such as HIPAA or local equivalents.
Understand support. Who answers at 2 a.m. when a study won't load? What are the response times in the contract?
Plan for the future. AI triage tools, mobile access, multi-site workflows and open-format archiving are all worth asking about.
When comparing PACS vendors, request references from hospitals similar to yours and call them. Ask what went wrong during implementation, not just what went well.
How Much Does a PACS System Cost?
Prices vary widely, so be wary of anyone quoting a single number. Costs depend on study volume, number of users, modalities, storage needs, deployment model and the vendor. In general:
- On-premise PACS has a large upfront cost for licenses, servers and installation, plus annual maintenance and IT staff time.
- Cloud PACS usually shifts the cost into a recurring subscription, often priced per study, per user or by storage.
- Hidden costs include interface work with your RIS and EHR, data migration from an old system, training, extra storage and downtime planning.
Ask for a total cost of ownership over five to seven years instead of comparing sticker prices. A cheap license can become expensive once you add everything around it.
What Are the Disadvantages of PACS?
PACS is a huge step forward, but it isn't perfect.
- Cost and complexity. Implementation takes time, money and project management.
- Downtime risk. If the system goes down, reading stops. You need failover and backup plans.
- Vendor lock-in. Proprietary archives make switching difficult.
- Migration pain. Moving years of studies between systems is slow and needs careful validation.
- Cybersecurity exposure. Medical imaging data is valuable, so security must be taken seriously.
- Change management. Staff need training, and some radiologists resist new workflows.
Good planning reduces most of these risks, but you should go in with eyes open.
How Do You Set Up a PACS System in a Hospital?
A typical rollout looks like this:
1. Define your needs. Gather radiologists, technologists, IT and administrators. List modalities, volumes, sites and integration points.
2. Set a budget and timeline. Include training, migration and contingency.
3. Shortlist vendors and run demos. Use your own sample studies and test the tricky cases.
4. Check references and contracts. Pay close attention to service levels, data ownership and exit terms.
5. Prepare the infrastructure. Confirm your network, storage and security setup, or your cloud connectivity.
6. Connect modalities and systems. Configure DICOM nodes, worklists and RIS/EHR interfaces.
7. Migrate historical data. Decide what moves, what stays archived and how you'll verify accuracy.
8. Train users. Do role-based training before go-live, not after.
9. Go live carefully. Many hospitals run the old and new systems in parallel for a short period.
10. Monitor and improve. Gather feedback, fix workflow bottlenecks and review performance regularly.
Rushing the planning phase is the most common mistake. The technology rarely fails; the workflow does.
Final Thoughts
A PACS system is more than an image storage box. It shapes how fast patients get answers, how comfortable your radiologists are, and how flexible your organization can be in the future. Whether you choose on-premise, cloud based PACS or a hybrid, focus on workflow, integration, security and open data access. Talk to real users, test with real studies and think about the next ten years, not just the next one.
Do that, and your PACS will quietly do what it should: get the right image to the right person at the right time.
 Media Pack Download
 Newsletters
 Industrial Events



